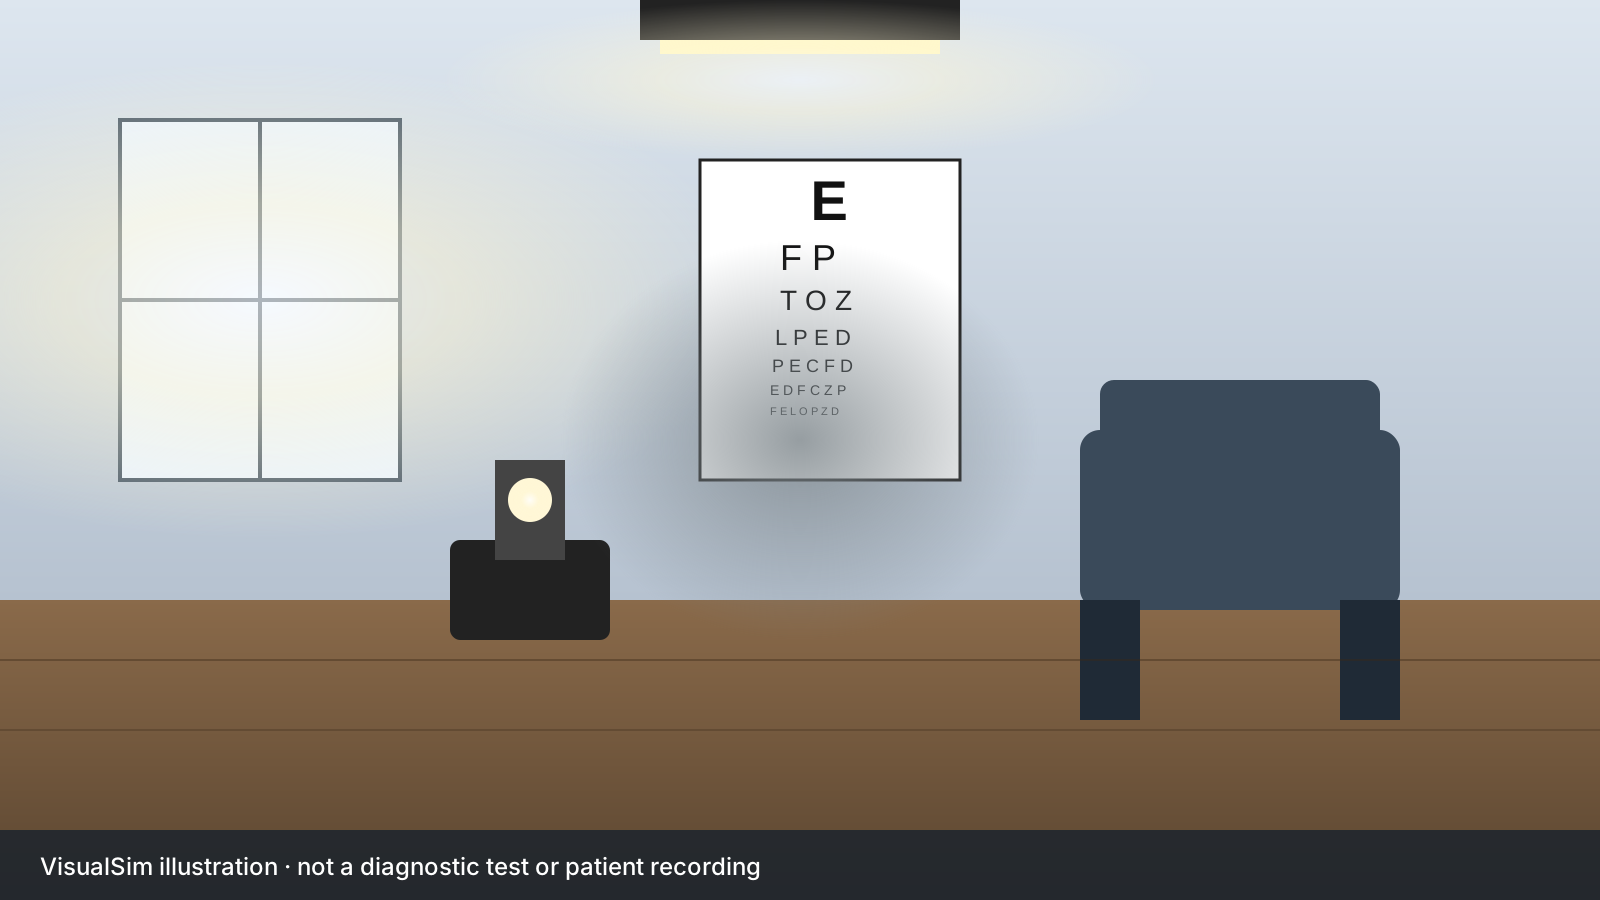
The macula supports detailed central vision
AMD affects the macula, the part of the retina used for detailed central tasks. Early disease may cause no noticeable symptoms. Later changes can include central blur, missing detail or straight lines appearing bent; peripheral vision can remain useful. [1]
Dry and wet AMD have different patterns and management. Wet AMD involves abnormal blood vessels and may change quickly. A symptom picture does not identify the type; retinal examination and imaging are important. [1]
Central tasks
Reading and recognizing faces may become difficult.
More than a black spot
Blur and distortion are useful descriptions too.
Type matters
Examination guides monitoring and treatment.
Terms in this guide
- Macula
- The retinal area important for detailed central vision.
- OCT
- Optical coherence tomography: imaging of tissue structure.
- Geographic atrophy
- A form of advanced atrophic AMD.
One condition. Different experiences.
These original illustrations show different central visual features. They are not a sequence of disease stages or a substitute for OCT imaging.
Original VisualSim schematic illustrations, informed by the cited clinical descriptions. These are not study figures, patient recordings or validated severity levels. Clinical basis: source 1. Artwork: © VisualSim; see image provenance.
A visual description is different from a retinal image
A retinal scan shows anatomy; a visual illustration suggests an experience. The two are not interchangeable. People may describe distorted lines, a smudge or missing detail, and awareness can differ between eyes and tasks. [2]
The simulator offers central blur and distortion. It does not measure retinal fluid, lesion size or the brain’s adaptation to missing information. Use the position controls to explain your description without assuming a dark circle is universal.
What can look similar?
Cataract or refractive blur
Several conditions can reduce clarity. Location and the examination help distinguish causes.
Metamorphopsia
Wavy lines are a symptom with several possible retinal causes, not an AMD diagnosis by themselves. [2]
A new change
New distortion or central loss warrants prompt assessment rather than waiting for a scheduled review. [1]
Similar-looking symptoms can have different causes. A matching picture cannot establish a diagnosis.
What an assessment may involve
Assessment may include visual acuity, a dilated retinal examination and OCT to look at macular structure. Further imaging depends on the findings. Ask which type of AMD is present and what changes should prompt urgent contact. [2]
- Describe each eyeMention whether a change seems different between eyes.
- Understand the findingsAsk what the scan shows and what it cannot explain about daily vision.
- Agree monitoringKnow your follow-up plan and the route for a new change.
What may help—and what is still being studied
Management depends on the type and stage. Anti-VEGF injections are used for wet AMD. AREDS2 supplements are appropriate only for selected AMD risk groups; they are not general vision supplements or a way to restore lost sight. [3]
Some geographic-atrophy medicines have regulatory approval in particular countries, including the United States. They aim to slow lesion growth, involve injections and have risks. Availability, eligibility and benefit need an individual retina-specialist discussion; it is inaccurate to say that all late dry AMD has no treatment options. [4]
For selected geographic atrophy, slowing lesion growth is different from restoring vision. OAKS and DERBY did not show a difference in key secondary visual-function outcomes at 24 months. Eligibility, injection risks and availability differ by treatment and country; ask which outcome a proposed treatment is expected to improve. [5]
What this can mean for daily life
Adapt detailed tasks
Discuss reading aids, contrast, lighting and low-vision rehabilitation for the activities that matter to you.
Make monitoring practical
Ask for instructions in a format you can use. This page’s examples are not a calibrated home monitoring chart.
Bring a clearer description to your appointment
Choose the questions you want to discuss. These choices stay in this page’s memory.
Research, with the context left in
Read supplements and geographic-atrophy studies in their eligible populations. A reduction in progression is different from restored vision.
What the evidence supports
Separate early/intermediate AMD, active neovascular AMD and geographic atrophy. The evidence supports timely anti-VEGF care for active neovascular disease and AREDS2 for selected AMD risk groups. Complement inhibitors can slow geographic-atrophy lesion growth in studied populations, but that anatomical result must not be presented as restored sight. Eligibility, injection burden, harms and regulatory availability differ by person and country.
How we select and interpret researchAAO: Age-Related Macular Degeneration Preferred Practice Pattern, updated 2026
Emphasizes prompt detection and anti-VEGF treatment of active neovascular AMD, smoking cessation and stage-appropriate AREDS2 supplementation. There is no evidence-based treatment for early AMD. Recent notes clarify US device authorizations without making every device suitable for every patient.
Limits and applicability: US-oriented guidance. A de novo device authorization is not a general efficacy endorsement, and home OCT or photobiomodulation must not be inferred to replace specialist monitoring or anti-VEGF care.
How to read this evidence: A strong clinical anchor because it synthesizes evidence and distinguishes disease stages; individual interventions still require their own benefit-harm assessment.
Chew et al.: AREDS2 Report 28 — long-term lutein/zeaxanthin and omega-3 outcomes
Findings supported substituting lutein/zeaxanthin for beta-carotene in AREDS supplements. Prior beta-carotene allocation was associated with a higher lung-cancer risk. Adding omega-3 fatty acids did not reduce progression in the main comparison.
Limits and applicability: All participants received AREDS2 in the extension, so the extension was not a continuing placebo-controlled supplement trial. Eligibility was AMD-specific; these are not general sight-enhancing supplements.
How to read this evidence: Large, well-characterized trial cohort supports the choice of lutein/zeaxanthin over beta-carotene, with important limitations in the post-trial comparison.
Heier et al.: Pegcetacoplan for geographic atrophy — OAKS and DERBY
Pegcetacoplan slowed geographic-atrophy lesion growth compared with sham at 24 months. There was no difference in the key secondary visual-function outcomes at that time. New exudative AMD occurred more frequently in treated groups.
Limits and applicability: Lesion area is not equivalent to restored vision or a predictable number of years of sight. Sponsor-funded studies and selected eligibility; postmarketing retinal vasculitis/vascular occlusion warnings must also be considered.
How to read this evidence: Stronger evidence for slowing the anatomical endpoint because of randomized sham comparisons; evidence for a patient-noticeable functional benefit is less certain.
Khanani et al.: Avacincaptad pegol for geographic atrophy — GATHER2
Monthly treatment slowed the prespecified square-root-transformed lesion-growth measure compared with sham. Macular neovascularization occurred in both groups and was more frequent with treatment.
Limits and applicability: The 12-month publication is not the entire later evidence base. Anatomical growth measures, treatment schedules and study populations must be stated; avoid direct efficacy rankings across different trials.
How to read this evidence: Randomization supports a treatment effect on lesion growth within the studied non-centerpoint-involving population; functional benefit and broader generalization require care.
FDA: IZERVAY prescribing information, including updated neovascular-AMD warning
The US indication is geographic atrophy secondary to AMD. The label describes intravitreal administration and risks including endophthalmitis, retinal detachment, pressure rise and neovascular AMD.
Limits and applicability: Jurisdiction-specific and subject to future revision. Access and eligibility differ internationally. Treatment discussions should use the current local label and all relevant safety information.
How to read this evidence: Authoritative for the stated US indication and warnings, but approval alone does not establish superiority or suitability for an individual patient.
Questions researchers still need to answer
- Is the outcome restored sight, slower visual decline, lesion growth or a laboratory measure?
- How closely do the trial’s disease stage, lesion position and eligibility match my situation?
- What are the absolute expected benefit, injection burden and serious harms?
- Is the treatment authorized and funded in my country, and which monitoring approach is appropriate?
These are editorial interpretations, not formal GRADE ratings or independent clinical review. A large sample, recent date or well-known publisher does not make every claim certain.
Trusted places to go next
Selected clinical references, research and support organizations. Each link explains who it is for.
Macular Society
Practical help, peer support and condition information.
AREDS/AREDS2 research
Who the trials studied and what supplement findings mean.
Organizations & ways to connect
Selected charities, professional organizations and communities, with their scope and region. Official pages checked 24 October 2026. Community discussions are peer support; each external service has its own privacy and moderation rules.
Macular Society
A helpline, local groups, telephone befriending, counselling, accessible information and research funding. Peer support shares lived experience and does not replace clinical assessment.
Connections listed by the organization.
Macular Disease Foundation Australia
Condition information, a national helpline, research and practical support. Eye Connect is for AMD and diabetes-related eye disease; people with other macular conditions can ask the helpline about suitable services.
Connections listed by the organization.
American Macular Degeneration Foundation
AMD education, research grants, caregiver materials, rehabilitation and practical living resources. Its official domain is macular.org.
Connections listed by the organization.
Fighting Blindness Canada
Funds retinal research and provides education, webinars and community events, including inherited-retinal-disease and AMD Coffee Connections. Community discussions are non-medical peer support.
Connections listed by the organization.
Retina International
A route to national retinal-disease groups, patient education, advocacy and research participation information. Member services vary by country; this is a global directory rather than a claim that every local group has been reviewed.
Connections listed by the organization.
RNIB
Accessible condition information, practical and emotional support, assistive technology and routes to community connection. Broader sight-loss support rather than a condition-specific medical service.
Connections listed by the organization.
Foundation of the American Society of Retina Specialists
Retina-specialist patient fact sheets, large-print and translated materials, a patient podcast and a specialist directory. Clinical education; not a peer-support group.
Questions you may still have
Does AMD always cause a black central hole?
No. Blur, distortion and missing detail can be experienced differently. A black circle is only a simplified illustration.
Can a slider distinguish wet from dry AMD?
No. Symptoms and images cannot replace retinal examination and imaging.
Should everyone take AREDS2?
No. Ask your clinician whether your disease stage and circumstances match the groups for whom it is appropriate. [3]
Sources, image credits and review status
Compiled by VisualSim from clinical references and published research. Sources checked 24 October 2026. Independent clinical review has not been recorded; no named clinical reviewer or clinical validation is claimed. Research evidence and its limitations are linked below.
- National Eye Institute. Age-related macular degeneration. Used for symptoms and types. Its broad late-dry-treatment wording is supplemented by current regulatory evidence below.
- American Society of Retina Specialists. AMD. Clinical information; sources checked 24 October 2026.
- National Eye Institute. AREDS/AREDS2 clinical trials. Clinical information; sources checked 24 October 2026.
- US FDA. Drug Trials Snapshots: IZERVAY. Regulatory evidence is jurisdiction-specific; not a prescribing recommendation.
- Heier et al. Pegcetacoplan for geographic atrophy: OAKS and DERBY (2023). Clinical information; sources checked 24 October 2026.
- AAO: Age-Related Macular Degeneration Preferred Practice Pattern, updated 2026 (2026). Specialist evidence-based clinical practice guideline; 2024 PPP with 2025 and 2026 clarifications
- Chew et al.: AREDS2 Report 28 — long-term lutein/zeaxanthin and omega-3 outcomes (2022). Ten-year epidemiologic follow-up of a randomized trial cohort; 3,882 participants
- Khanani et al.: Avacincaptad pegol for geographic atrophy — GATHER2 (2023). Randomized, double-masked, sham-controlled phase 3 trial; 448 randomized participants; initial 12-month report
- FDA: IZERVAY prescribing information, including updated neovascular-AMD warning (2025). Regulatory prescribing information summarizing indication, trials and harms
The simulator helps people communicate an experience. It cannot diagnose a condition, measure a visual field, or establish that someone is safe to drive.