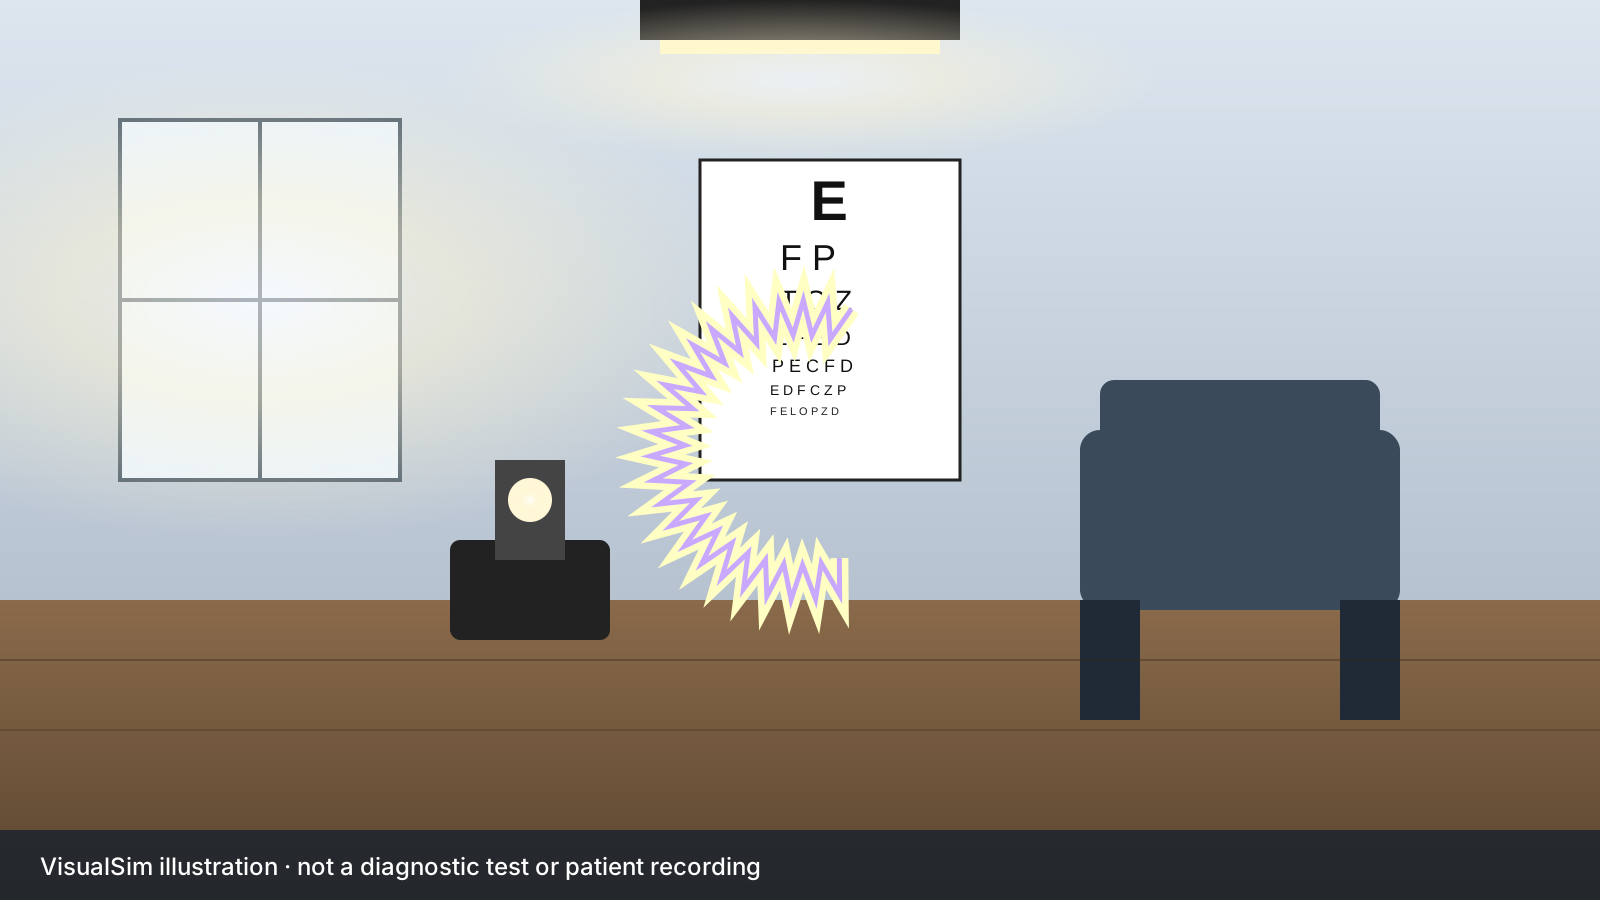
A visual event that changes over time
Typical migraine aura consists of fully reversible neurological symptoms. Visual changes often develop gradually and can include positive phenomena, such as shimmering edges, and negative phenomena, such as missing detail. Individual symptoms commonly last 5–60 minutes, but diagnosis considers the complete pattern and alternatives. [1]
A systematic review found many reported visual appearances, including zigzags, bright spots, foggy vision and water-like distortion. A classic C-shaped arc is useful for illustration, but should not be treated as the only possible aura. [2]
Time course
Describe how an episode starts, spreads and ends.
More than zigzags
Several visual phenomena can occur.
First or changed
A clinician may need to exclude another cause.
Terms in this guide
- Positive phenomenon
- Something added to vision, such as a shimmering edge.
- Scotoma
- An area of reduced or missing visual sensitivity.
One condition. Different experiences.
These original illustrations show different arc positions. They are not a diagnostic sequence, a clinical clock or a prediction of what comes next.
Original VisualSim schematic illustrations, informed by the cited clinical descriptions. These are not study figures, patient recordings or validated severity levels. Clinical basis: source 1. Artwork: © VisualSim; see image provenance.
What explains the changing pattern?
Cortical spreading depolarization is a leading explanation for typical aura. It is a change in activity across the cortex, rather than a shape physically moving through the eye. Research descriptions are more varied than the familiar fortification-spectrum drawing. [3]
The simulator draws an adjustable arc. It does not measure cortical activity, blood flow or the risk of a stroke. A symptom affecting only one eye, a sudden onset or a substantially changed pattern deserves assessment rather than automatic attribution to a known migraine history. [1]
What can look similar?
Visual snow
Continuous static has a different time course from a discrete typical aura. The conditions can coexist. [3]
Retinal or vascular symptoms
One-eye visual loss and sudden negative symptoms require careful assessment. Similar appearances do not establish the cause. [1]
Occipital seizures
Some visual episodes have other neurological explanations. Duration, accompanying symptoms and clinical assessment matter. [3]
Similar-looking symptoms can have different causes. A matching picture cannot establish a diagnosis.
What an assessment may involve
Describe onset, spread, duration, whether symptoms remain when either eye is covered, and any sensory, speech or headache symptoms. A clinician decides whether examination or investigation is needed; online criteria should not be used to dismiss an atypical episode. [1]
- Record the sequenceA timeline can be more useful than one still image.
- Describe the whole episodeInclude accompanying symptoms and recovery, not only its most striking visual moment.
- Agree a planAsk what to do during familiar attacks and which changes should prompt urgent assessment.
What may help—and what is still being studied
Care depends on the confirmed diagnosis and the impact of attacks. Acute and preventive migraine approaches have different roles and should be discussed with a clinician. An aura illustration cannot determine a medicine, dose or whether a new episode is safe to manage at home. [4]
Describe frequency, disability and any change from your established pattern. The practical goal is an individualized management plan, rather than making the visual example match perfectly.
What this can mean for daily life
Describe an episode safely
Write or sketch the experience after you are safe and able to do so. Do not test your vision by driving or navigating hazards.
Make the timeline clear
Bring the start time, approximate duration and recovery pattern. Note what was different from previous episodes.
Bring a clearer description to your appointment
Choose the questions you want to discuss. These choices stay in this page’s memory.
Research, with the context left in
Research separates the variety of visual descriptions from the criteria used to diagnose a syndrome. Neither validates an online image as a diagnostic test.
What the evidence supports
Aura has a well-established clinical classification and a substantial descriptive literature. Strong evidence for preventing migraine headache should be separated from the smaller, less certain evidence about preventing aura itself. New, abrupt or unusual symptoms must not be diagnosed by matching the animation.
How we select and interpret researchICHD-3: 1.2 Migraine with aura
Aura symptoms are fully reversible and commonly develop gradually. Visual aura may occur with other neurologic symptoms and can occur without headache.
Limits and applicability: The familiar 5–60-minute description applies to an individual typical aura symptom; it is not an absolute rule for every episode or a safe waiting period for new symptoms. Clinical assessment must consider mimics.
How to read this evidence: An authoritative clinical framework, not a rule that can safely distinguish migraine from stroke on a website.
Viana and colleagues: Clinical features of visual migraine aura—a systematic review
Aura can include zigzags, bright flashes, blind spots, foggy vision and heat-wave or water-like distortions. One expanding arc does not capture every experience.
Limits and applicability: Recall, selected study populations and inconsistent labels limit comparisons. The review does not validate a simulator or give the probability that a particular visual symptom is migraine.
How to read this evidence: Useful synthesis for the diversity of visual experiences; symptom-frequency estimates are less secure because study methods and descriptions differed.
Thomsen and colleagues: Clinical features of migraine with aura—a REFORM study
Visual aura was reported by 215 participants. Some people had sensory or language symptoms and the timing relative to headache varied.
Limits and applicability: Participants had at least four monthly migraine days and many received specialist care. This is not a representative population sample and the analysis itself did not prospectively record every aura attack.
How to read this evidence: Useful detailed clinical characterization with standardized interviews, but limited generalizability from a predominantly female tertiary-clinic sample.
American Headache Society: CGRP-targeting therapies as a first-line migraine-prevention option
The society considers CGRP-targeting treatments a first-line preventive option alongside existing approaches, without requiring prior failure of another class.
Limits and applicability: This is a United States position statement; eligibility, contraindications, licensing and reimbursement vary. It does not establish that these treatments stop aura or that every person with aura needs medication.
How to read this evidence: Substantial evidence supports the general migraine-prevention indication discussed by the statement. Confidence cannot be transferred automatically to an aura-specific effect.
Effects of erenumab on migraine aura frequency: a REFORM study
Aura days decreased during preventive treatment and remained below baseline during follow-up in this selected cohort.
Limits and applicability: Placebo response, natural fluctuation and regression to the mean cannot be separated from treatment. The sample was predominantly female and selected for frequent aura. Prior studies were inconsistent; randomized aura-specific trials remain needed.
How to read this evidence: Useful new aura-specific evidence with prospective diaries, but low confidence in a causal treatment effect because there was no blinded control group.
Questions researchers still need to answer
- Which preventive treatments reduce aura frequency, duration and disability in randomized studies with aura-specific endpoints?
- How do visual, sensory, language and aura-without-headache presentations differ across the life course?
- Can prospective symptom diaries improve recall without encouraging unsafe self-diagnosis of stroke or retinal disease?
These are editorial interpretations, not formal GRADE ratings or independent clinical review. A large sample, recent date or well-known publisher does not make every claim certain.
Trusted places to go next
Selected clinical references, research and support organizations. Each link explains who it is for.
ICHD-3: migraine with aura
Formal diagnostic framework to discuss with a clinician.
The Migraine Trust
Plain-language information and practical support.
Visual aura research review
Detailed descriptions and the methods behind the review.
American Migraine Foundation
Education and support alongside professional care.
Organizations & ways to connect
Selected charities, professional organizations and communities, with their scope and region. Official pages checked 24 October 2026. Community discussions are peer support; each external service has its own privacy and moderation rules.
American Migraine Foundation
Doctor-verified education, care navigation and the Move Against Migraine Facebook community. The community is for support and shared experience, not diagnosis or individualized treatment; check its membership and moderation rules before joining.
Connections listed by the organization.
The Migraine Trust
Migraine information, a support service, research, advocacy and guidance on school and work. Contact details and service availability are maintained on its own site.
Migraine Australia
Australian migraine education, advocacy and support navigation. Useful for understanding local access and patient experiences; resources cover migraine broadly, not aura alone.
Migraine Canada
Education, support-group information, care navigation and practical Canadian disability and access resources. Social feeds share organizational updates and are not a clinical consultation.
Connections listed by the organization.
European Migraine and Headache Alliance
Find national patient organizations, advocacy initiatives and headache-care resources across countries. Membership and local services vary; not every association offers clinical care.
Connections listed by the organization.
Questions you may still have
Can aura occur without a headache?
Yes. Headache is not required for every aura episode. A first or unusual episode still needs assessment. [1]
Does the arc always expand like this?
No. This represents one common visual description; the research literature documents many others. [2]
Can the slider time an aura?
No. Progression changes an illustration. Slider values and animation speed are not clinical time measurements.
Sources, image credits and review status
Compiled by VisualSim from clinical references and published research. Sources checked 24 October 2026. Independent clinical review has not been recorded; no named clinical reviewer or clinical validation is claimed. Research evidence and its limitations are linked below.
- International Headache Society. ICHD-3: Migraine with aura. Clinical information; sources checked 24 October 2026.
- Viana et al. Clinical features of visual migraine aura: a systematic review (2019). Review of 14 studies; no figure is reproduced.
- Differential Diagnosis of Visual Phenomena Associated with Migraine: Spotlight on Aura and Visual Snow Syndrome (2023). Clinical information; sources checked 24 October 2026.
- Diagnosis and acute management of migraine (2023). Clinical information; sources checked 24 October 2026.
- Thomsen and colleagues: Clinical features of migraine with aura—a REFORM study (2024). Cross-sectional analysis of structured interviews within a prospective registry; 227 adults with migraine with aura
- American Headache Society: CGRP-targeting therapies as a first-line migraine-prevention option (2024). Professional-society position statement drawing on randomized trials and real-world migraine-prevention evidence
- Effects of erenumab on migraine aura frequency: a REFORM study (2026). Prospective, single-center, open-label cohort; 80 adults with frequent diary-confirmed aura analyzed over treatment and follow-up
The simulator helps people communicate an experience. It cannot diagnose a condition, measure a visual field, or establish that someone is safe to drive.