Seeing something that is not in the scene
Charles Bonnet syndrome describes visual hallucinations associated with sight loss. Images can range from simple patterns to people, animals or scenes. People often recognize that the images are not really present. [1]
When the explanation is CBS, the visual experiences do not themselves mean someone has a mental illness. New hallucinations should still be discussed with a clinician rather than self-diagnosed from an example. [2]
Visual
The experience can be simple or highly detailed.
Varied
Content, size, position and duration can differ.
Worth discussing
A clear description helps a clinician assess the cause.
Terms in this guide
- Visual hallucination
- A visual experience without a corresponding external object.
- Insight
- Awareness that an image is not actually present in the scene.
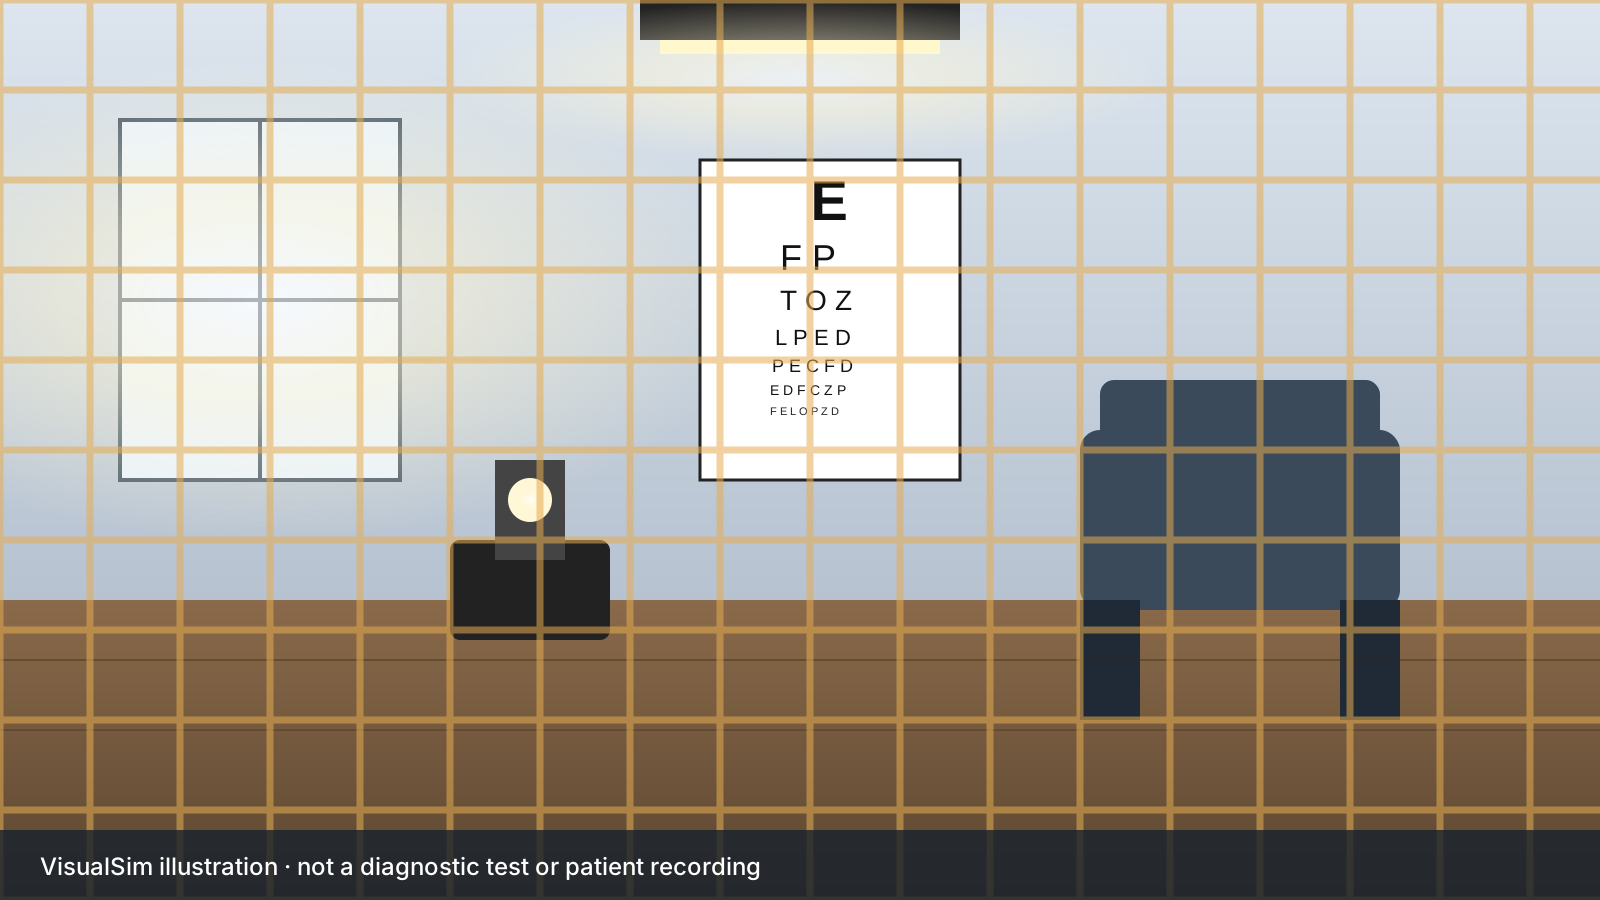
One condition. Different experiences.
Images are not limited to one appearance. These original illustrations use the existing simulator; optional published reconstructions appear later in the research section.
Original VisualSim schematic illustrations, informed by the cited clinical descriptions. These are not study figures, patient recordings or validated severity levels. Clinical basis: source 1. Artwork: © VisualSim; see image provenance.
Sight loss and visual processing
CBS is associated with reduced visual input. One explanation is that changes in input allow internally generated visual activity to become experienced as images. This is a broad explanatory model, not something our simulator measures. [1]
A 2024 study examined brain chemistry and functional connectivity in people with CBS. Such mechanistic research can inform hypotheses without supplying a single diagnostic brain test or a complete explanation for everyone. [3]
What can look similar?
Other hallucination causes
A clinician may consider medicines, neurological illness and other explanations. A visual similarity alone cannot separate them. [2]
Illusions
An illusion involves misinterpreting something that is present. Describe whether an image appears independently of the real scene. [1]
Floaters and flashes
Describe small drifting shadows or brief flashes separately from formed imagery, especially when these symptoms are new.
Similar-looking symptoms can have different causes. A matching picture cannot establish a diagnosis.
What an assessment may involve
It can help to explain both the visual experiences and any sight loss. Describe the images, how long they last, your awareness that they are not real, and any other symptoms. [2]
- Tell the storyWhat appears? How often? What happens just before or after?
- Review the contextDiscuss changes in vision, medicines, health and the impact on daily life.
- Agree a support planAsk who to contact, what changes matter and what support is available.
What may help—and what is still being studied
Understanding the condition and discussing it openly can reduce distress. Eye care and low-vision support may help people make the most of their remaining sight. There is no single treatment that reliably stops CBS for everyone. [1]
Ask about an individualized support plan and what to do if the images change or become distressing. A proposed medicine or coping approach should be discussed with its evidence and risks, rather than presented as a universal treatment. [2]
What this can mean for daily life
Describe without judgement
Let people choose their own words. A family member can use an example to understand what is being described, without insisting it must look like the picture.
Make support easy to find
Low-vision services and specialist CBS support can complement clinical care. A plain-language explanation may help a family member understand the experience without assuming that the person is confused.
Bring a clearer description to your appointment
Choose the questions you want to discuss. These choices stay in this page’s memory.
Research, with the context left in
Research images can make experiences easier to discuss, but how they were created matters. The example below was reconstructed from reports using AI, rather than captured from vision.
Show research reconstructions (some imagery may be unsettling)
Participant reports, reconstructed for research
The authors used DALL-E 3 to illustrate participant descriptions. These are AI-generated reconstructions, not patient photographs or direct recordings of perception. The chart shows NEVHI interview scores incorporating frequency, duration and distress.
Bridge et al. Therapeutic Advances in Ophthalmology (2024), Figure 2. Unmodified. Original paper · CC BY 4.0
What the evidence supports
CBS research supports better recognition and reassurance after appropriate assessment, with substantial variation in reported prevalence between care settings. Small mechanistic studies and one small placebo-controlled stimulation trial are scientifically useful but do not establish a routine drug or home-device treatment. Support should address sight loss, distress, daily function and stigma.
How we select and interpret researchChristoph and colleagues: Prevalence of Charles-Bonnet syndrome in ophthalmic patients—a systematic review and meta-analysis
The pooled estimate was about one in ten across the included ophthalmic populations, with higher estimates in vision-rehabilitation settings.
Limits and applicability: A pooled average is not an individual risk or a population-wide estimate for every person with sight loss. Publication in 2025 does not mean the search includes all 2024–2025 research.
How to read this evidence: Useful broad synthesis showing that CBS is clinically relevant; confidence in a single universal prevalence figure is limited by different definitions, recruitment settings and patient groups.
daSilva Morgan and colleagues: tDCS for visual hallucinations in CBS—a randomized placebo-controlled crossover trial
Active stimulation reduced hallucination frequency relative to placebo in this trial. Hallucination-impact ratings improved in both conditions.
Limits and applicability: Findings do not establish a lasting benefit, identify all responders or exclude uncommon harms. Specialist-supervised research is not a recommendation for a consumer or home stimulation device.
How to read this evidence: A stronger design than a case report, but confidence in routine clinical effectiveness and safety is limited by the very small sample and need for replication.
daSilva Morgan and colleagues: Visual cortical activity in CBS—testing the deafferentation hypothesis
Group differences in visual-cortical responses were consistent with altered excitability after sight loss.
Limits and applicability: A small cross-sectional study cannot prove a universal causal mechanism, provide an individual diagnostic scan or determine a treatment. Its inhibitory-stimulation work used the same CBS cohort as the earlier treatment trial, so those results are not independent replication.
How to read this evidence: Useful converging mechanistic evidence using imaging, EEG and stimulation measures; preliminary for individual prediction or diagnosis.
Bridge and colleagues: Neurochemistry and functional connectivity in the brain of people with CBS
Examines brain chemistry and connectivity alongside hallucination reports. Its illustrated reconstructions help communicate variation in experience.
Limits and applicability: Small-group mechanistic associations do not establish an individual cause or treatment. Figure 2 uses DALL-E 3 reconstructions informed by participant reports, not photographs of hallucinations or clinical imaging; the interview chart combines symptom dimensions.
How to read this evidence: Useful hypothesis-generating work and an explicitly attributed source of symptom illustrations; not clinical validation of a simulator.
Jones and Moosajee: Visual hallucinations and sight loss in children and young adults
Describes CBS presentations in younger people and highlights recognition and support needs.
Limits and applicability: A case series cannot estimate how common CBS is in children, establish that their risk equals adults’ risk or determine an optimal treatment.
How to read this evidence: Useful evidence that CBS is not confined to older adults, with limited evidence about frequency or prognosis.
Questions researchers still need to answer
- Can more consistent diagnostic definitions and direct questions reduce under-reporting without mislabelling delirium, medication effects or other neurologic conditions?
- Which education, sight-rehabilitation and psychological-support approaches reduce distress and improve daily function in controlled studies?
- Will larger blinded stimulation trials reproduce the early signal, with longer follow-up and adequate safety assessment?
- What support works best for children, people with mild or asymmetric sight loss, and people with limited access to eye care?
These are editorial interpretations, not formal GRADE ratings or independent clinical review. A large sample, recent date or well-known publisher does not make every claim certain.
Trusted places to go next
Selected clinical references, research and support organizations. Each link explains who it is for.
RNIB: Charles Bonnet syndrome
A practical explanation for people with sight loss and those supporting them.
NHS: Charles Bonnet syndrome
Symptoms, assessment and advice on seeking help.
American Academy of Ophthalmology
An additional clinical patient guide for families and carers.
Esme’s Umbrella
Information and support focused on living with Charles Bonnet syndrome.
Read the 2024 brain research paper
Methods, results and the context behind the reproduced study figure.
Organizations & ways to connect
Selected charities, professional organizations and communities, with their scope and region. Official pages checked 24 October 2026. Community discussions are peer support; each external service has its own privacy and moderation rules.
Esme’s Umbrella
CBS awareness, support, information for children and adults, and research advocacy. Its support can complement sight-loss services and assessment; it cannot establish the cause of a new hallucination.
Macular Society
CBS information, a support service and counselling or peer-support navigation. Its CBS counselling eligibility extends beyond macular disease; check current age, location and referral conditions on the host site.
Connections listed by the organization.
Royal National Institute of Blind People
Accessible CBS information and downloadable formats, with practical and emotional sight-loss support. General sight-loss support remains useful even when symptoms do not fit a single cause.
Connections listed by the organization.
Charles Bonnet Syndrome Foundation Australia
Dedicated CBS information, support, translations and links to a Facebook community. Social content and personal stories are for connection, not diagnosis; check the host’s privacy and participation rules.
Connections listed by the organization.
Vision Australia
Practical low-vision services, assistive technology and community support, with CBS information and signposting. Service availability depends on location and eligibility; it is broader than CBS.
Connections listed by the organization.
Questions you may still have
Does this mean someone has dementia?
CBS associated with sight loss is not itself a diagnosis of dementia. A clinician should assess new hallucinations and any additional symptoms. [2]
Can children experience CBS?
Yes. It has been reported in children and young adults with sight loss. [4]
Why does the page hide one study figure?
Some reconstructed imagery may be unsettling. It is optional and clearly labelled so readers can choose whether to view it.
Sources, image credits and review status
Compiled by VisualSim from clinical references and published research. Sources checked 24 October 2026. Independent clinical review has not been recorded; no named clinical reviewer or clinical validation is claimed. Research evidence and its limitations are linked below.
- RNIB. Charles Bonnet syndrome. Patient information; accessed 24 Oct 2026.
- NHS. Charles Bonnet syndrome. Patient information and advice on assessment.
- Bridge et al. Neurochemistry and functional connectivity in the brain of people with Charles Bonnet syndrome (2024). Figure 2 reproduced under CC BY 4.0. DALL-E 3 reconstructions, explicitly labelled above.
- Jones and Moosajee. Visual hallucinations and sight loss in children and young adults: a retrospective case series of Charles Bonnet syndrome (2021). Clinical case series, not a prevalence study.
- Esme’s Umbrella. Charles Bonnet syndrome support. Specialist support; separate from primary research.
- Christoph and colleagues: Prevalence of Charles-Bonnet syndrome in ophthalmic patients—a systematic review and meta-analysis (2025). Systematic review and meta-analysis of 49 studies including 20,303 ophthalmic patients; search conducted in June 2023
- daSilva Morgan and colleagues: tDCS for visual hallucinations in CBS—a randomized placebo-controlled crossover trial (2022). Randomized, double-masked, placebo-controlled crossover trial with 16 participants
- daSilva Morgan and colleagues: Visual cortical activity in CBS—testing the deafferentation hypothesis (2025). Multimodal cross-sectional study comparing 19 people with CBS and 18 age/visual-acuity-matched eye-disease controls
The simulator helps people communicate an experience. It cannot diagnose a condition, measure a visual field, or establish that someone is safe to drive.